
This vignette sets out the statistics behind respondeR: the cut-point approach, how responder probabilities and their variances are computed, each pooling method, the relative measures, the threshold-free common-language effect size, the standardized-mean-difference bridge, random effects, threshold uncertainty, multi-arm trials, and the assumptions and their limits. It closes with a guide to choosing a method and a note on how version 0.2.0 differs from 0.1.0.
The cut-point approach
For one study arm with mean change , standard deviation and a minimal important difference (MID) threshold , assume the patient-level change is Normally distributed. A responder is a patient whose change crosses the threshold. The responder probability is
or when a lower change is better. This is the cut-point (“dichotomization”) method reviewed by Thorlund and colleagues (2011) and detailed by Anzures-Cabrera, Sarpatwari & Higgins (2011). The between-arm contrast is then a familiar binary effect measure.
respondeR evaluates the requested tail directly on the log scale
(pnorm(..., log.p = TRUE)), so
and
keep full precision even when
is far below machine precision. Risk ratios and odds ratios are computed
from these log probabilities, never from a clamped
.
Sampling variance of a responder probability
The arm mean and SD are estimates, so is too. By the delta method, with for the Normal model,
where is the inverse Mills ratio, computed as so it stays finite in the tails. The logit scale uses . For the Student- and lognormal models the gradients are numerical (central differences of ) and the joint sampling distribution of uses the model’s own third and fourth central moments :
For the Normal model these reduce to and 0. These are first-order (large-sample) formulas. In finite samples the sampling variance of an SD converges slowly under heavy tails or skew, so for the () and lognormal models the intervals tend to be somewhat too wide in the tails of the distribution. A model with degrees of freedom has no finite fourth moment; the Normal-theory value is then used, which makes the intervals much too narrow, and respondeR warns. Treat the non-Normal models as sensitivity analyses.
Each per-arm variance is floored at half a patient’s resolution, with , so that a probability deep in a tail (whose model-based variance underflows) can never receive an infinite weight.
The pooling methods
Studies report per-arm summaries; the methods differ in how those are combined. Study contributes and .
Individual (recommended)
Dichotomize each study, form its contrast, then pool. Every comparison stays within a randomized study. With and as above, , and the log risk ratio and log odds ratio are differences of exact log probabilities.
The per-study variance follows se_method:
-
"delta"(default): the delta-method variances above, which carry the uncertainty in the reported mean and SD. -
"binomial": the pseudo-binomial , which treats the model-based probability as if it were an observed proportion of dichotomized patients (the version 0.1.0 default).
Fixed effects. The risk difference is pooled with
sample-size weights
(the Mantel-Haenszel risk difference weights), with variance
(rd_weights = "sample_size", the default). Inverse-variance
weights (rd_weights = "inverse_variance") let any study
whose responder probabilities sit near 0 or 1, and so whose model-based
variance is tiny, dominate the pooled risk difference, which is exactly
what happens in an ordinary MID sweep. The log risk ratio and log odds
ratio are pooled by inverse variance.
responder_analysis(sample_responder_data, mid = 1, method = "individual")
#> Responder analysis (respondeR)
#>   MID = 1 (a higher change is a response); k = 3 studies; fixed
#>   effects; delta per-study variance
#>   Percentages; 95% confidence intervals.
#>
#>      Method PE PC                  RD                  RR                  OR
#>  Individual  -  - 25.5 (20.0 to 31.0) 2.15 (1.79 to 2.58) 3.20 (2.45 to 4.18)
#>                    NNT
#>  NNTB 3.9 (3.2 to 5.0)
#>
#> Use as.data.frame() for every column, summary() for details, plot() for a forest plot.
respondeR warns whenever one study holds more than half of the weight for a pooled measure (with three or more studies).
Weighted mean
Pool the summaries, then dichotomize. respondeR pools the
control mean and the within-study mean
difference separately by inverse variance (fixed or random
effects, following pooling), and sets the experimental mean
to their sum:
with and (plus under random effects). Each arm’s SD is the within-study pooled SD .
The estimator depends on every study’s arm means and SDs, including
through the SD-dependent weights and the pooled SDs. Its sampling
covariance is the full Jacobian form
over all arms, where
holds the derivatives of the arm responder probabilities (on the
probability, log and logit scales) with respect to that arm’s mean and
SD, and
is the joint sampling covariance of the arm mean and SD under the chosen
distribution (including their covariance for the skewed lognormal
model). Because the control arm enters both pooled means, the two are
negatively correlated, and the Jacobian carries that automatically.
Under random effects the between-study variances of the two pooled
means,
with normalized weights
,
are added; with
and a Wald interval the result equals the fixed-effect one.
ci_method = "hksj" or "hksj_adhoc" multiplies
the variance path of each pooled mean by its HKSJ factor
(scaling its gradient by
,
which keeps the joint covariance positive semidefinite) and uses a
critical value. The between-study variances are held at their
estimates.
Anchoring on the within-study difference matters. Pooling the two arms separately (as version 0.1.0 did) compares patients across studies and can show a Simpson’s-paradox bias when allocation ratios differ between studies (Altman and Deeks, 2002):
paradox <- data.frame(
  study = c("A", "B"), change_e = c(2.5, 0.5), sd_e = 1, n_e = c(400, 20),
  change_c = c(2.0, 0.0), sd_c = 1, n_c = c(20, 400)
)
responder_rd_individual(paradox, mid = 1)[, c("study", "rd")]
#>   study         rd
#> 1     A 0.09184805
#> 2     B 0.14988228
as.data.frame(responder_analysis(paradox, mid = 1,
  method = c("individual", "weighted")))[, c("method", "rd")]
#>       method        rd
#> 1 individual 0.1208652
#> 2   weighted 0.1600305
Separate arm pooling gave a risk difference of about 0.74 here, although neither trial shows more than 0.15.
In a simulation (1000 replicates; 10 studies of 100 patients per arm;
Normal change scores with SD 1; control means drawn from
;
a mean difference of 0.5, fixed or drawn from
;
MID 1), the 95 percent weighted interval covered the realized-study
target at 0.94 to 0.96 with fixed effects and the population target at
0.93 to 0.96 with random effects. With 5 studies the random-effects Wald
interval covered at 0.91, and with ci_method = "hksj_adhoc"
at 0.96.
Unweighted mean and median
Dichotomize the arithmetic mean or the median of the study means and SDs. These are descriptive robustness summaries with no variance model, so respondeR reports point estimates only.
Baseline risk: matched or median control
By default (control = "matched") the control proportion
comes from the same pooled summaries. The simulation study that
motivated this package (Sofi-Mahmudi, 2024) held the baseline risk at
the median control arm; that is available as
control = "median". For the weighted method the
experimental mean is then the median control mean plus the pooled
within-study difference. Point estimates only.
responder_analysis(sample_responder_data, mid = 1, control = "median")
#> Responder analysis (respondeR)
#>   MID = 1 (a higher change is a response); k = 3 studies; fixed
#>   effects; delta per-study variance
#>   Percentages; 95% confidence intervals.
#>
#>           Method   PE   PC                  RD                  RR
#>       Individual    -    - 25.5 (20.0 to 31.0) 2.15 (1.79 to 2.58)
#>    Weighted mean 47.3 21.5                25.8                2.20
#>  Unweighted mean 47.7 21.5                26.2                2.22
#>           Median 48.7 21.5                27.2                2.26
#>                   OR                   NNT
#>  3.20 (2.45 to 4.18) NNTB 3.9 (3.2 to 5.0)
#>                 3.27              NNTB 3.9
#>                 3.32              NNTB 3.8
#>                 3.46              NNTB 3.7
#>
#> Use as.data.frame() for every column, summary() for details, plot() for a forest plot.
Relative effect measures and the NNT
Confidence intervals for RR and OR are formed on the log scale. Following Altman (1998), a positive risk difference is reported as a number needed to treat for one more responder (NNTB) and a negative one as a number needed to treat for one fewer (NNTH); when the risk-difference interval includes zero the NNT interval passes through infinity and is printed in that form.
The responder risk ratio deserves care. When responders are common in the control arms, is close to 0 with a small variance, so the pooled risk ratio is compressed toward 1. The odds ratio is symmetric in responders and non-responders and, under the cut-point model, closer to constant across baseline risks; it is the default route for summary-of-findings tables.
Summary-of-findings rows
responder_sof() applies the pooled relative effect to an
assumed control risk and reports, per 1000 patients, the control risk,
the intervention risk and the difference with their intervals (Guyatt
and colleagues, 2013). The default control risk is the median
control-arm responder probability:
ind <- responder_analysis(sample_responder_data, mid = 1, method = "individual")
responder_sof(ind, control_risk = c(0.1, 0.3))
#> Summary of findings (responders)
#>
#>      Method Control risk         Intervention risk
#>  individual 100 per 1000 262 per 1000 (214 to 317)
#>  individual 300 per 1000 578 per 1000 (512 to 642)
#>                                Difference        Relative effect
#>  162 more per 1000 (114 more to 217 more) OR 3.20 (2.45 to 4.18)
#>  278 more per 1000 (212 more to 342 more) OR 3.20 (2.45 to 4.18)
Common-language effect size (threshold-free)
The common-language effect size (CLES, the probabilistic index) is the probability that a randomly chosen treated patient has a better change than a randomly chosen control. Under a Normal model it is exact:
Per-study are pooled by inverse variance and back-transformed. It is a population-level probability, not the chance that treatment helps a particular patient.
cles <- responder_cles(sample_responder_data)
c(cles = cles$cles, lb = cles$cles_lb, ub = cles$cles_ub)
#>      cles        lb        ub
#> 0.6899041 0.6505162 0.7272252
The SMD bridge (method = "smd")
The second approach of Anzures-Cabrera et al. (2011) pools the
standardized mean difference and maps it to an odds ratio. respondeR
pools Hedges’
and uses the logistic-distribution conversion
(Hasselblad and Hedges, 1995; Chinn, 2000). (The Cox conversion uses a
factor of about 1.65 instead of
.)
The odds ratio interval is the pooled
interval transformed, so ci_method applies. Risks follow
from the pooled control risk
:
.
Because
is itself estimated, the risk-difference and risk-ratio intervals use
the delta method with
and
,
including the covariance between
and the pooled control mean. That covariance comes from the full
Jacobian of the within-study sampling errors; under random effects the
same correlation is assumed between the pooled
and the pooled control mean (an assumption with a visible effect on the
risk-difference interval), and the control mean is pooled with a Wald
variance while ci_method applies to
.
The prediction interval is transformed to the risk-difference scale at
.
responder_analysis(sample_responder_data, mid = 1, method = "smd")
#> Responder analysis (respondeR)
#>   MID = 1 (a higher change is a response); k = 3 studies; fixed
#>   effects; delta per-study variance
#>   Percentages; 95% confidence intervals.
#>
#>          Method   PE   PC                  RD                  RR
#>  SMD (logistic) 50.1 22.1 28.1 (22.1 to 34.1) 2.27 (1.89 to 2.73)
#>                   OR                   NNT
#>  3.55 (2.69 to 4.69) NNTB 3.6 (2.9 to 4.5)
#>
#> Use as.data.frame() for every column, summary() for details, plot() for a forest plot.
Converting a pooled effect fitted elsewhere
responder_from_effect() applies the same bridge to a
single pooled effect, for example from a published meta-analysis, given
a baseline control responder risk; responder_analysis()
calls it for you when you pass a metafor rma
object, and reads the arms directly when you pass a
meta::metacont object. The effect is taken as experimental
minus control and oriented by direction, so a pain
reduction with direction = "lower" raises the responder
risk. For a mean difference the experimental proportion is the control
probability shifted along the Normal cut-point,
which needs a reference within-arm SD
(sd_ref). With a fixed baseline probability the intervals
are conditional on it, as in a GRADE summary-of-findings table; with an
estimated baseline (a mean, SD and
)
its uncertainty is propagated jointly with that of the effect. See
vignette("meta-analysis-objects") for worked examples.
Random effects and heterogeneity
The individual, weighted and SMD methods can use random effects
(pooling = "random") with DerSimonian-Laird or REML
(tau_method = "REML", via metafor) between-study
variance. Cochran’s
,
and
are inverse-variance based and refer to the scale that is pooled: the
risk difference for individual, Hedges’
for smd.
Three interval methods are available for the pooled estimate:
-
"wald": Normal critical value; can under-cover with few studies. -
"hksj": Hartung-Knapp-Sidik-Jonkman, a interval scaled by the observed dispersion. When the studies agree more closely than their within-study variances predict, it can be much narrower than Wald. -
"hksj_adhoc": HKSJ with the ad hoc floor of Rover, Knapp and Friede (2015), never narrower than Wald. Recommended when there are few studies.
near_identical <- data.frame(
  study = 1:4, change_e = c(1, 1.01, 0.99, 1), sd_e = 1, n_e = 100,
  change_c = 0, sd_c = 1, n_c = 100
)
sapply(c("wald", "hksj", "hksj_adhoc"), function(ci) {
  r <- responder_analysis(near_identical, mid = 0.5, method = "individual",
                          pooling = "random", ci_method = ci)
  r$rd_ub - r$rd_lb
})
#>       wald       hksj hksj_adhoc
#> 0.10356253 0.00914819 0.16815726
The prediction interval is
,
where
is the variance that built the confidence interval, for every
tau_method (Higgins, Thompson and Spiegelhalter, 2009). It
is not reported for fewer than three studies and is unstable for small
.
Uncertainty in the MID
If the threshold is itself estimated, mid_sd treats it
as uncertain. The MID is one threshold shared by every
study and both arms, so its uncertainty is fully correlated across
studies. respondeR pools without it and then adds it once, through the
derivative of the whole pooled estimator with respect to the MID:
It therefore does not change the weights,
or the point estimate, and it does not shrink as studies are added. A
complementary approach is to report the results across a range of
thresholds with responder_curve():
plot(responder_curve(sample_responder_data, mids = seq(0, 2, by = 0.25)), at = 1)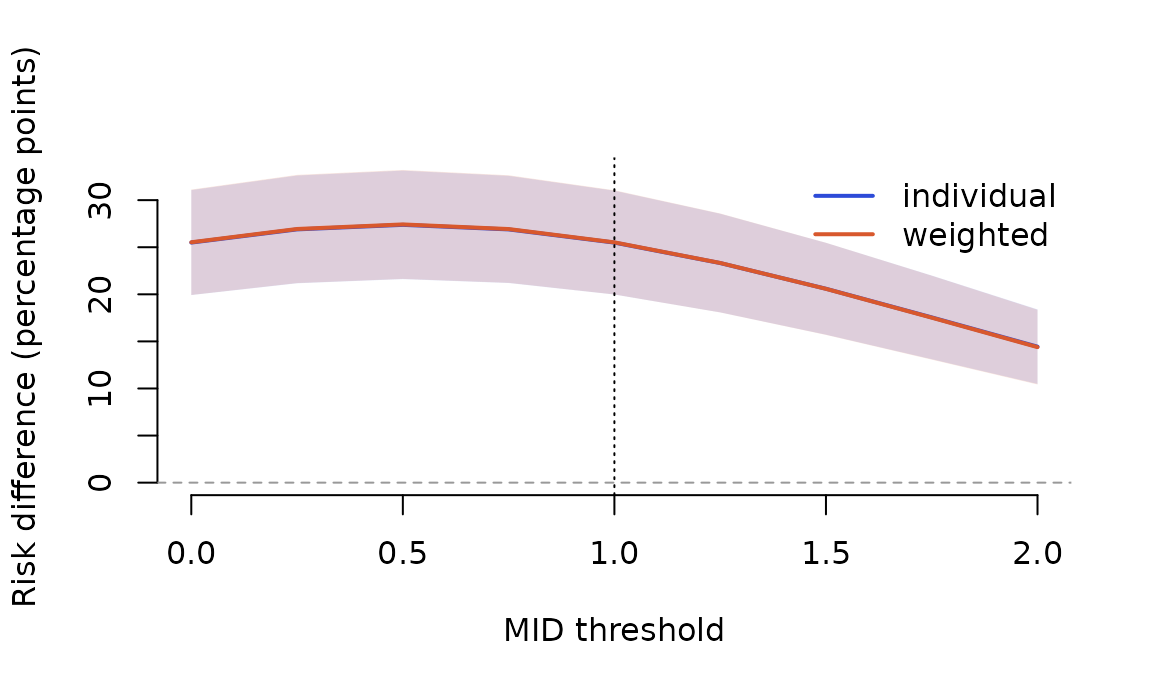
The bands are pointwise.
Multi-arm trials
A trial with two active arms and one control contributes two
comparisons that reuse the same control patients. Entering them as
independent studies counts those patients twice and overstates the
precision. Mark such comparisons with a trial column: when
comparisons of one trial share an identical control arm, respondeR
divides the control sample size equally among them (Cochrane Handbook,
section 23.3.4). The bundled vas_pain data use this for two
three-arm trials.
Final values and absolute thresholds
A responder can also be defined by the outcome reaching an absolute
state, for example a pain score of 3 or less at follow-up, rather than
by a change. The same cut-point model applies to the final-value
distribution: put the final means and SDs in the
change_e/change_c columns and the absolute
threshold in mid. The interpretation differs (the
proportion in the target state, not the proportion who improved by the
MID), so label the analysis accordingly.
final <- data.frame(
  study = c("A", "B"), change_e = c(2.6, 3.1), sd_e = c(1.9, 2.1), n_e = c(60, 45),
  change_c = c(3.8, 4.2), sd_c = c(2.0, 2.2), n_c = c(58, 47)
)
# Proportion with a final pain score of 3 or less (lower is better).
responder_analysis(final, mid = 3, direction = "lower", method = "individual")
#> Responder analysis (respondeR)
#>   MID = 3 (a lower change is a response); k = 2 studies; fixed effects;
#>   delta per-study variance
#>   Percentages; 95% confidence intervals.
#>
#>      Method PE PC                  RD                  RR                  OR
#>  Individual  -  - 21.7 (11.2 to 32.1) 1.67 (1.29 to 2.18) 2.47 (1.57 to 3.89)
#>                    NNT
#>  NNTB 4.6 (3.1 to 8.9)
#>
#> Use as.data.frame() for every column, summary() for details, plot() for a forest plot.
Interval options
-
ci_type = "logit"builds the weighted method’s risk-difference interval by the MOVER method from logit-scale arm intervals, allowing for their correlation, so it stays within . It also applies toresponder_rd_individual(). Pooledindividualandsmdintervals are formed on the scale that is pooled. A nonzeromid_sdcorrelates the arms in a way MOVER cannot carry, so Wald intervals are used, with a warning. -
dist = "lognormal"or"t"changes the change-score model as a sensitivity analysis for skewed or heavy-tailed data.
Assumptions and limitations
-
Change-score distribution. The probabilities assume
a parametric model for the patient-level change within each arm. Means
and SDs alone cannot establish that the model fits; skewed outcomes can
bias the responder proportions. Use
distas a sensitivity analysis. - Summary-statistic input. Only means, SDs and sample sizes are used.
- Choice of MID. Results depend on the threshold. Report the MID, show the curve across plausible thresholds, and consider the threshold-free CLES.
- Normal-approximation intervals. Wald intervals can misbehave for extreme proportions or tiny samples, and the delta method is a first-order approximation.
Choosing a method
| If you want… | Use |
|---|---|
| A defensible default that keeps comparisons within trials | individual |
| A pool-then-dichotomize estimator with an interval | weighted |
| A descriptive robustness summary |
median / unweighted (point estimates) |
| A cross-check through a different bridge to risks | smd |
| Few studies, random effects | pooling = "random", ci_method = "hksj_adhoc" |
| To show threshold dependence | responder_curve() |
| A GRADE summary-of-findings row | responder_sof() |
| To avoid choosing a threshold | responder_cles() |
Changes from version 0.1.0
Version 0.2.0 changes several results. The per-study variance
defaults to the delta method; fixed-effect risk differences use
sample-size weights; ratio measures use exact log probabilities; MID
uncertainty is added after pooling; the weighted method anchors on the
within-study difference; the SMD intervals keep the chosen interval
method and the control-risk uncertainty; prediction intervals follow one
rule; and shared control arms of multi-arm trials are split.
se_method = "binomial", rd_weights = "inverse_variance"
reproduces the version 0.1.0 individual point estimate.
Relation to the thesis
The thesis behind this package (Sofi-Mahmudi, 2024) evaluated the median, unweighted, weighted and individual strategies by simulation, pooling means and SDs by inverse variance and converting a pooled risk ratio to a risk difference with a representative baseline risk. The estimators here follow its framework but differ in detail (the pooled SD, the anchored weighted method, the variance models and the interval options), so the thesis simulations do not validate every option in this package.
References
Sofi-Mahmudi, A. (2024). Identifying an optimal strategy for converting pain as a continuous outcome to a responder analysis [Master’s thesis, McMaster University]. MacSphere. https://hdl.handle.net/11375/30210
Thorlund, K., Walter, S. D., Johnston, B. C., Furukawa, T. A., & Guyatt, G. H. (2011). Pooling health-related quality of life outcomes in meta-analysis: a tutorial and review of methods for enhancing interpretability. Research Synthesis Methods, 2(3), 188 to 203. doi:10.1002/jrsm.46
Anzures-Cabrera, J., Sarpatwari, A., & Higgins, J. P. T. (2011). Expressing findings from meta-analyses of continuous outcomes in terms of risks. Statistics in Medicine, 30(25), 2967 to 2985. doi:10.1002/sim.4298
Altman, D. G. (1998). Confidence intervals for the number needed to treat. BMJ, 317(7168), 1309 to 1312.
Altman, D. G., & Deeks, J. J. (2002). Meta-analysis, Simpson’s paradox, and the number needed to treat. BMC Medical Research Methodology, 2, 3.
Chinn, S. (2000). A simple method for converting an odds ratio to effect size for use in meta-analysis. Statistics in Medicine, 19(22), 3127 to 3131.
Guyatt, G. H., Oxman, A. D., Santesso, N., et al. (2013). GRADE guidelines: 12. Preparing summary of findings tables: binary outcomes. Journal of Clinical Epidemiology, 66(2), 158 to 172.
Hasselblad, V., & Hedges, L. V. (1995). Meta-analysis of screening and diagnostic tests. Psychological Bulletin, 117(1), 167 to 178.
Higgins, J. P. T., Thompson, S. G., & Spiegelhalter, D. J. (2009). A re-evaluation of random-effects meta-analysis. Journal of the Royal Statistical Society: Series A, 172(1), 137 to 159.
McGraw, K. O., & Wong, S. P. (1992). A common language effect size statistic. Psychological Bulletin, 111(2), 361 to 365.
Rover, C., Knapp, G., & Friede, T. (2015). Hartung-Knapp-Sidik-Jonkman approach and its modification for random-effects meta-analysis with few studies. BMC Medical Research Methodology, 15, 99. doi:10.1186/s12874-015-0091-1